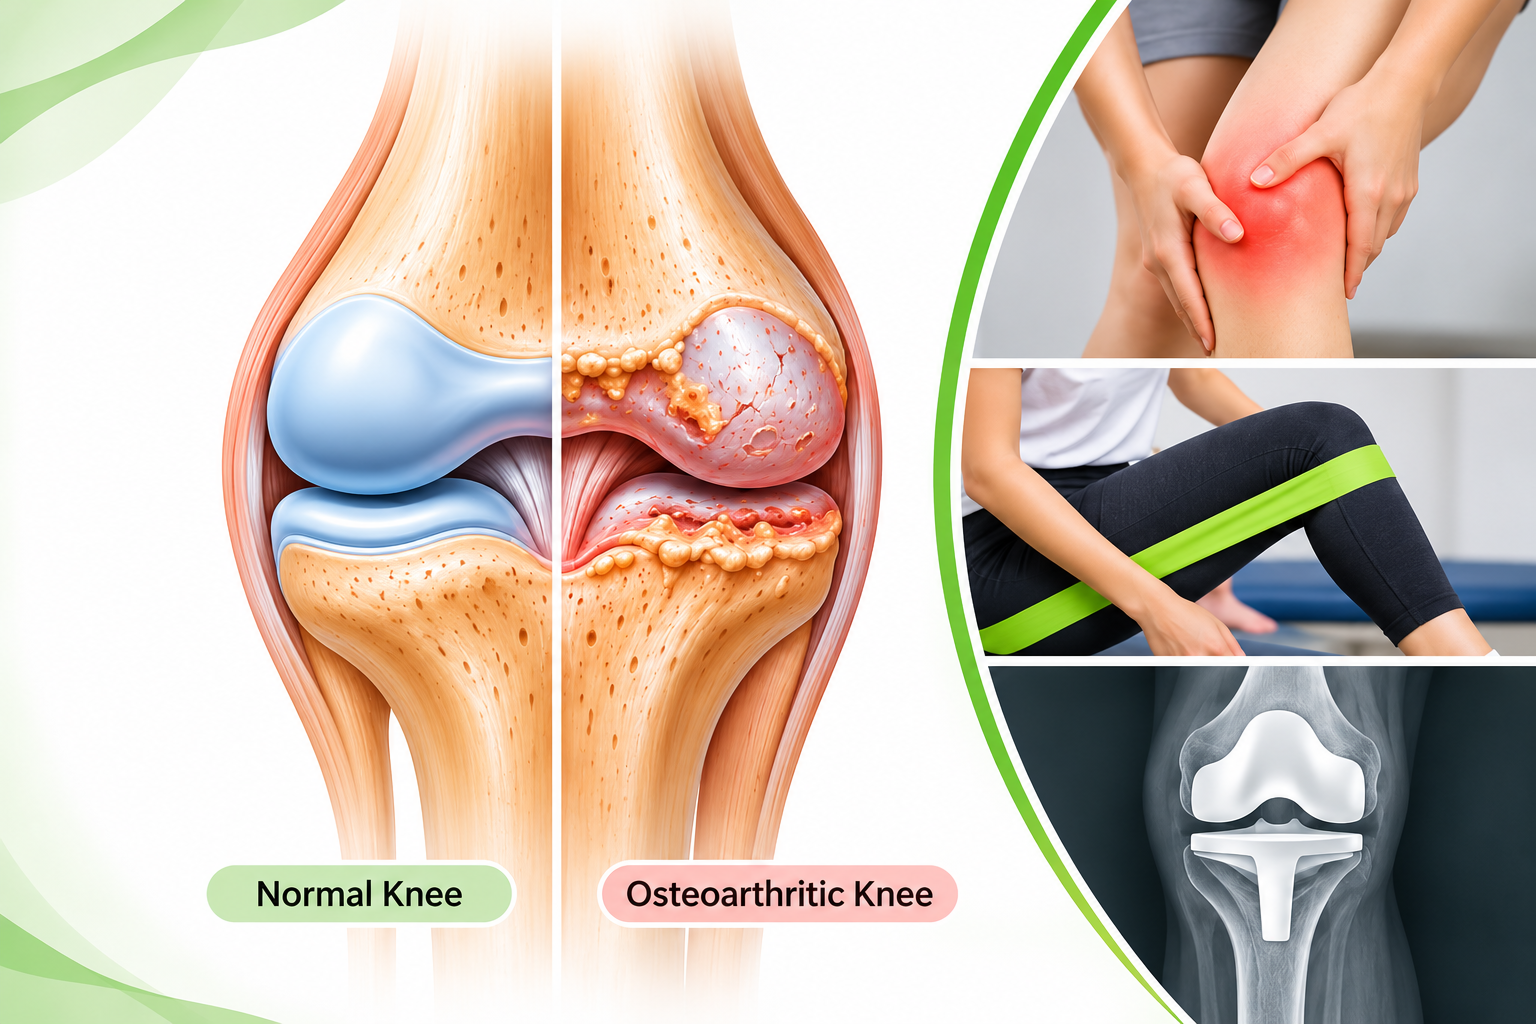
Knee osteoarthritis (OA) is a chronic, whole-joint disorder characterised by structural changes involving articular cartilage, subchondral bone, synovium, menisci and surrounding tissues. It is a major cause of pain, stiffness and functional limitation, particularly in older adults.
Activities such as walking, climbing stairs, squatting and rising from a chair may become increasingly difficult as symptoms progress. However, radiographic changes do not always correspond to the severity of symptoms.
Although established OA cannot currently be reliably reversed, appropriate medical management and structured physiotherapy can significantly improve pain, physical function and quality of life.
1. Understanding the Normal Knee Joint
The knee is a modified hinge-type synovial joint consisting of two main articulations:
- Tibiofemoral joint: Formed by the femoral condyles and tibial plateau.
- Patellofemoral joint: Formed by the posterior surface of the patella and the femoral trochlea.
The major anatomical structures include:
- Articular cartilage: A smooth, specialised hyaline cartilage covering the joint surfaces. It reduces friction and distributes compressive forces.
- Medial and lateral menisci: Fibrocartilaginous structures that improve joint congruency, distribute load and contribute to shock absorption.
- Synovial membrane: Lines the inner surface of the joint capsule and produces synovial fluid.
- Joint capsule and ligaments: Provide passive stability and guide joint movement.
- Quadriceps and hamstrings: Contribute to knee movement, dynamic stability and functional loading.
A healthy knee depends on the coordinated function of these structures to allow efficient weight-bearing and movement.
2. What Happens in Knee Osteoarthritis?
Osteoarthritis is not simply the wearing away of cartilage. It is a complex biological and mechanical process involving the entire joint.
The development of OA involves several interconnected changes:
- Articular cartilage degeneration: Changes in the cartilage extracellular matrix affect its normal composition and mechanical properties. Cartilage becomes progressively damaged, irregular and less effective at distributing loads.
- Subchondral bone remodelling: The bone beneath the articular cartilage undergoes altered remodelling. Sclerosis and changes in bone structure may develop.
- Osteophyte formation: Bony projections, known as osteophytes, may form around joint margins.
- Synovial inflammation: Low-grade synovitis may occur and contribute to pain, swelling and joint irritability.
- Meniscal and other soft-tissue changes: Meniscal degeneration, extrusion and ligamentous changes may contribute to altered joint loading and instability.
- Muscle weakness and functional decline: Pain, reduced physical activity and impaired neuromuscular function may contribute to quadriceps weakness, reduced endurance and difficulty performing daily activities.
These changes can develop gradually and vary considerably between individuals.
3. Types of Knee Osteoarthritis
A. According to aetiology
- Primary OA: Develops without a clearly identifiable preceding joint injury or disease. Age, genetic susceptibility, body composition and cumulative joint loading may contribute.
- Secondary OA: Develops in association with an identifiable factor, such as previous trauma, fracture, ligament injury, meniscal damage, joint infection or certain metabolic conditions.
B. According to the affected compartment
- Medial compartment OA: Involves the medial tibiofemoral compartment.
- Lateral compartment OA: Involves the lateral tibiofemoral compartment.
- Patellofemoral OA: Affects the articulation between the patella and femur.
- Multicompartmental OA: Involves two or more compartments.
C. Radiographic classification: Kellgren–Lawrence grading
The Kellgren–Lawrence system is commonly used to classify radiographic OA severity:
| Grade | Radiographic Features |
|---|---|
| 0 | No radiographic features of OA |
| 1 | Doubtful joint-space narrowing and possible osteophytes |
| 2 | Definite osteophytes, with possible joint-space narrowing |
| 3 | Multiple osteophytes, definite narrowing, sclerosis and possible bony deformity |
| 4 | Large osteophytes, marked narrowing, severe sclerosis and definite bony deformity |
Clinical relevance: Radiographic severity does not necessarily reflect pain intensity or functional disability. Treatment should be guided by symptoms, physical function and clinical findings rather than the X-ray grade alone.
4. Risk Factors
Knee OA is multifactorial. Important risk factors include:
- Increasing age.
- Overweight and obesity.
- Previous knee trauma, including ACL and meniscal injuries.
- Genetic predisposition.
- Repetitive occupational or sporting joint loading.
- Lower-limb malalignment, including varus and valgus alignment.
- Previous joint surgery.
- Certain metabolic and systemic conditions.
These factors may interact rather than act independently.
5. Clinical Presentation and Assessment
Common signs and symptoms
Patients may present with:
- Activity-related knee pain, often aggravated by weight-bearing.
- Morning stiffness, commonly lasting 30 minutes or less.
- Stiffness following prolonged sitting or inactivity.
- Joint swelling or effusion.
- Crepitus during movement.
- Reduced knee flexion or extension.
- Reduced quadriceps strength.
- Difficulty walking, climbing stairs, squatting or standing for prolonged periods.
Clinical assessment by a physiotherapist
A comprehensive assessment should include:
- Subjective examination: Location, duration and behaviour of pain; aggravating and relieving activities; morning stiffness and symptom fluctuations; previous injuries, surgery and medical history; functional limitations and activity level; sleep, confidence, fear of movement and patient goals.
- Objective examination: Observation of posture, lower-limb alignment and gait; knee range of motion, particularly terminal extension; joint effusion and swelling assessment; quadriceps, hamstring and hip muscle strength; patellofemoral and tibiofemoral examination where indicated; functional movement assessment; balance and walking capacity.
Useful outcome measures
| Measure | Clinical Purpose |
|---|---|
| WOMAC | Pain, stiffness and physical function |
| KOOS | Symptoms, pain, daily function and quality of life |
| Timed Up and Go (TUG) | Functional mobility |
| 30-Second Chair Stand Test | Lower-limb functional strength |
| 6-Minute Walk Test | Walking capacity and endurance |
| Numeric Pain Rating Scale | Pain intensity |
Use consistent assessment procedures to monitor progress over time.
6. Medical Management
The medical management of knee OA aims to control symptoms, maintain function and support participation in rehabilitation.
- Topical NSAIDs: Topical diclofenac and other appropriate NSAID preparations are commonly recommended for knee OA.
- Oral NSAIDs: May be considered when topical treatment is ineffective or unsuitable. Gastrointestinal, renal, hepatic and cardiovascular risks must be considered by the prescribing clinician.
- Intra-articular corticosteroid injections: May provide short-term symptom relief in selected patients and can sometimes help facilitate participation in therapeutic exercise.
- Other medication: Selected patients may be considered for additional pain-management options depending on their clinical circumstances and relevant guidelines.
Medication should be prescribed or recommended by an appropriately qualified medical practitioner. It does not replace exercise-based management.
7. Physiotherapy Management: The Foundation of Rehabilitation
Physiotherapy is central to the conservative management of knee OA. The primary objective is not to regenerate damaged cartilage, but to improve the patient's capacity to move, tolerate loading and participate in daily activities.
Current clinical guidance identifies patient education, therapeutic exercise and appropriate weight management as foundational interventions[cite: 1, 2].
A. Patient education and self-management
Patient education should be provided from the beginning of rehabilitation. Explain that:
- OA does not mean the patient must stop moving.
- Appropriate exercise is generally beneficial.
- Temporary discomfort during exercise does not automatically indicate joint damage.
- Long-term exercise adherence is important.
- Weight management may improve symptoms when excess weight is present.
- Rehabilitation focuses on improving function and independence.
Address fear of movement, misconceptions about cartilage damage and unrealistic expectations about treatment. Education should support self-management rather than create dependence on repeated passive treatment.
B. Progressive strengthening exercises
Muscle strengthening is one of the most important components of knee OA rehabilitation. The programme should target the entire lower limb rather than concentrating exclusively on the quadriceps.
- Quadriceps strengthening: Essential for knee extension, shock absorption and functional activities (e.g., quadriceps isometric contractions, straight-leg raises, seated knee extensions, resisted knee extension, sit-to-stand exercises).
- Hamstring strengthening: Contribute to knee control and lower-limb function (e.g., resisted knee flexion, hamstring curls, appropriate closed-chain exercises).
- Hip strengthening: Hip abductors and extensors contribute to pelvic control and lower-limb movement (e.g., side-lying hip abduction, hip extension exercises, resistance-band lateral walking, bridging).
- Calf strengthening: Contribute to gait, propulsion and lower-limb functional capacity (e.g., supported heel raises, standing calf raises, progressive resisted plantar flexion).
Exercise selection and resistance should be adjusted according to the patient's symptoms, strength and functional capacity.
C. Range of motion and mobility exercises
Maintaining knee mobility is important for walking, transfers and stair negotiation. Common interventions include heel slides for knee flexion, active knee extension, assisted knee extension where indicated, gentle stretching when muscle tightness limits movement, and stationary cycling with appropriate seat height and resistance.
Clinical priority: Terminal knee extension. An extension deficit can affect the ability to achieve an efficient stance phase during gait and may interfere with standing and functional loading. Assess extension carefully rather than concentrating only on knee flexion.
D. Aerobic conditioning
Aerobic exercise improves cardiovascular fitness, endurance and general physical capacity. Appropriate options include walking, stationary cycling, aquatic exercise, swimming, and other tolerable low-impact activities. The exercise mode should reflect the patient's preferences, cardiovascular status, pain response and functional capacity.
E. Neuromuscular and balance training
Knee OA may be associated with impaired balance, reduced proprioceptive performance and altered movement strategies. Interventions may include weight-shifting exercises, supported single-leg standing, step training, dynamic balance exercises, functional reaching activities, and controlled changes of direction. Balance training is particularly relevant for older adults and patients with a history of falls or reduced confidence during walking.
F. Weight management
For patients who are overweight or obese, weight management should be incorporated into the rehabilitation plan. Excess body weight increases mechanical demands on the knee, while weight reduction can improve pain and physical function. A combined approach involving appropriate exercise, sustainable dietary changes and behavioural support is preferable. A physiotherapist can support activity planning and collaborate with a dietitian or medical practitioner when needed.
G. Gait and functional training
Improvement in isolated muscle strength must translate into better functional performance. Functional rehabilitation should address walking pattern and speed, sit-to-stand performance, stair ascent and descent, squatting where appropriate, step length and lower-limb control, and community mobility and daily activity tolerance. A walking aid, such as a cane, may be appropriate for selected patients. Correct fitting and instruction are essential.
H. Manual therapy: An adjunct, not the main treatment
Selected joint mobilisation and soft-tissue techniques may be considered when they help improve movement or facilitate exercise. However, manual therapy should be used alongside therapeutic exercise. Evidence does not support relying on manual therapy alone for long-term OA management[cite: 1].
I. Symptom management and activity modification
Depending on the patient's presentation, advice may include relative modification of aggravating activities during symptom flares, appropriate pacing of daily activities, heat for temporary relief of stiffness, cold applications for short-term symptom relief when helpful, and education on balancing activity and recovery. Passive modalities should not replace progressive exercise.
Evidence note: NICE recommends against routinely offering TENS, therapeutic ultrasound, interferential therapy, laser therapy and several other electrotherapy modalities for OA because evidence of benefit is insufficient. These should not be presented as core treatments[cite: 1].
8. Important Clinical Considerations That Can Be Overlooked
Good physiotherapy is not simply prescribing quadriceps exercises. Clinical reasoning, reassessment and appropriate progression are essential:
- Assess joint effusion: Swelling contributes to arthrogenic muscle inhibition, reducing quadriceps activation. Assess swelling and modify loading when necessary.
- Do not overlook terminal knee extension: A persistent extension deficit impairs gait mechanics and functional performance.
- Examine the entire kinetic chain: Assess the hip, ankle and foot in addition to the knee.
- Differentiate muscle weakness from pain-related inhibition: Identify whether poor performance stems from pain, effusion, or true loss of strength.
- Do not prescribe the same exercise programme to everyone: Tailor selection to irritability, severity, baseline capacity, and preferences.
- Monitor the response to loading: Track how the knee responds during exercise, later that day, and by the next session.
- Consider psychological and behavioural factors: Address fear of movement, self-efficacy, sleep, anxiety, and depression.
- Use objective outcome measures: Record baseline findings and reassess functional improvements regularly.
- Teach self-management: Ensure patients can continue exercising independently and manage flares.
- Reassess instead of repeating treatment without review: Evolve the rehabilitation plan based on the patient's ongoing clinical response.
9. Surgical Management
Surgery may be considered when symptoms substantially affect quality of life and appropriate non-surgical management has been ineffective or unsuitable.
- High Tibial Osteotomy (HTO): A joint-preserving procedure changing tibial alignment to redistribute load across the medial compartment with varus alignment.
- Unicompartmental Knee Arthroplasty (UKA): Replaces the affected compartment while preserving native compartments.
- Total Knee Arthroplasty (TKA): Replaces damaged surfaces with prosthetic components for advanced symptomatic disease.
Arthroscopic washout or debridement is not routinely recommended for uncomplicated knee OA. The decision for joint replacement should be based on symptoms, functional limitation, clinical assessment and patient preferences—not solely on radiographic grading[cite: 1].
Physiotherapy before and after surgery
- Preoperative rehabilitation (prehabilitation): Improve muscle strength, maintain ROM, enhance walking capacity, and educate the patient.
- Postoperative rehabilitation: Early mobilisation, pain/effusion control, extension restoration, progressive strengthening, gait training, balance work, and functional recovery.
10. Can Knee Osteoarthritis Be Cured?
There is currently no established treatment that reliably reverses established knee OA or restores the joint to its original anatomical condition. However, symptoms and functional limitations can often be improved substantially through education, progressive exercise, weight management, medical support, and functional rehabilitation.
Conclusion
Knee osteoarthritis is a whole-joint disorder requiring a comprehensive and individualised management approach. Physiotherapy plays a central role through patient education, progressive strengthening, aerobic conditioning, mobility training, balance rehabilitation and functional exercise. Successful outcomes depend on accurate assessment, appropriate exercise dosage, monitoring of symptom response, regular reassessment and long-term patient participation.
Ready to Take Control of Your Knee Health?
Explore structured, evidence-based online physiotherapy guidance tailored to your specific recovery goals with PhysioCare.
Book Your Online AssessmentReferences
- National Institute for Health and Care Excellence (NICE). Osteoarthritis in over 16s: diagnosis and management. NICE Guideline NG226. London: NICE; 2022. Available from: https://www.nice.org.uk/guidance/ng226[cite: 1]
- Agency for Care Effectiveness, Singapore. Management of knee osteoarthritis: A joint effort with patients. ACE Clinical Guideline. 2026. Available from: https://www.ace-hta.gov.sg/healthcare-professionals/ace-repository-for-clinical-guidelines/management-of-knee-osteoarthritis---a-joint-effort-with-patients-acg/[cite: 2]
- American Academy of Orthopaedic Surgeons (AAOS). Management of Osteoarthritis of the Knee (Non-Arthroplasty). Evidence-Based Clinical Practice Guideline. 3rd ed. 2021. Available from: https://www.aaos.org/quality/quality-programs/osteoarthritis-of-the-knee/[cite: 3]
- Bannuru RR, Osani MC, Vaysbrot EE, et al. OARSI guidelines for the non-surgical management of knee, hip, and polyarticular osteoarthritis. Osteoarthritis Cartilage. 2019;27(11):1578–1589. doi:10.1016/j.joca.2019.06.011[cite: 4].
- Kolasinski SL, Neogi T, Hochberg MC, et al. 2019 American College of Rheumatology/Arthritis Foundation Guideline for the Management of Osteoarthritis of the Hand, Hip, and Knee. Arthritis Care Res (Hoboken). 2020;72(2):149–162. doi:10.1002/acr.24131.
Medical Disclaimer: This article is intended for general educational purposes only. It does not replace an individual medical diagnosis, clinical examination or personalised physiotherapy assessment. Treatment decisions should be based on the patient's clinical presentation and appropriate professional evaluation. Author: PhysioCareOnline Editorial Team